A request for comment from people living with life-limiting diagnoses:

I am developing a workshop for the general population on creating a healthier relationship to mortality- and I want to amplify the voices of those engaged in the confrontation.

If there is something that you feel you want the wider culture to understand about living with life limiting illness, but is hard to get others to hear or withstand,

and you want me to share it in workshop- please contact me here or through my website

https://t.co/nFdzkoyWLx
What do you feel the culture does not understand about the labors of confronting mortality? What do you have to protect others from about your experience? What do you have to edit away from people who think this will never happen to them?
So much of what is talked about in these space, is offered by people who are vicariously impacted, or who are trying to stay near

What would you want your wider community to integrate and understand about your experience that they turn away from?
I will attribute your comments to you in the workshop, or I can keep them anonymous if you prefer.
I know what my own experience was like living post-diagnosis- I know that I learned to hide things and edit and protect myself and others from the way I now saw the world and the medical and existential tasks that preoccupied me. But I am one person, with my own viewpoint.
“Nothing about us without us” doesn’t often extend into explorations of death and dying. Because we are sick, fatigued, or need to protect our energies by not wasting our breath

Or because we die and others may posthumously edit or misperceive what we wanted them to understand
You can tweet, DM (I’ll open my DM’s for the day) or email me:

https://t.co/nFdzkoyWLx
For example: I found the binary notion that I was either “dying” and my life was over or seemed “just fine and cured” completely exhausting.

Almost no one could grasp that I was living on chemotherapy for 3 years , with attending limitations, with no clear prognosis.
People who had been told repeatedly that I was on chemo would be stunned when I turned down a drink and reminded them I was on chemo yet AGAIN.
“oh! But I thought you were all done with that!”
Or chemobrain, I would sometimes want to scream at people who wanted me to remember trivial details or process information quickly or who simply did not seem to ACCEPT that I was cognitively altered by the meds

“You seem fine! Your writing is so clear”
Anyway: my DMs will be open for a day or two for those who want to share privately.

And cancer isn’t the only life-limiting experience, just the one I’ve experienced.
Here is another one:

“WOW! You look great!” is more about the relief of your own fears than any comfort to me.
You were just bracing yourself to see me as gaunt and wasting.

Also: this is no criticism, just truth. I have absolutely done this to others even post-diagnosis.

I catch myself now and say: “I just feel so happy to see your face- its been too long.”
In case you are confronting a life-threatening diagnosis and seeing this and don’t follow me and are thinking: “why should I tell this stranger anything?” I am living in the in-between too:

https://t.co/F81qjskepY
I'll add one more. This one is dicey- because I don't mean to negate anyone's pain or suffering - here goes:

The voices of caretakers & the bereaved unwittingly drown out the voices of the potentially dying.I know because I've been a caretaker and survived many loved ones.
and I realized that once I was diagnosed myself, that my fear of losing my loved one, and the responsibility I felt for protecting them was important and excruciating -

but not the same labor as preparing to say goodbye to everything and everyone, including my own identity.
My attempts to share my own process would often stir up absolutely understandable grief in those who were mourning their own losses.

But too often, the tables would turn to my needing to comfort them, and my own work would have to continue in isolation.
Both sides of the experience of loss are important - and I don't mean to minimize anyone's grief.

I just think that the work of mourning one person and the work of mourning every one and everything are similar but different.
And I know that I absolutely could not see this distinction clearly for my loved ones as they died.
There are things we share standing at the edge of the abyss.

But there are things that only those preparing to actually go over the edge contend with.

More from Health

@73inlancs @janethooton_ @ErinInTheMorn @fifi_EY 1/ The 🏴󠁧󠁢󠁥󠁮󠁧󠁿 government decided pediatric gender care in England would be a monopoly contract (a Labour minister, in 2008), despite all other NHS patients officially being entitled to a choice of providers, & second opinions on diagnoses & treatment, & gave it to GIDS, which has…

@janethooton_ @ErinInTheMorn @fifi_EY 2/…always advocated that trans minors & their families must have no alternative source of care, & subsequent Tory ministers have personally put their signature on renewals of it, and even personally rejected proposals for improvement that have been put forward by NHS England…

@janethooton_ @ErinInTheMorn @fifi_EY 3/…as a result of wider & public consultation. They & their civil servants listen only to GIDS on trans minors - it was GIDS advised against <18s being allowed #GenderRecognition in 2004, & since, on the basis that no one under 18 can be certain of their gender identity, just…

@janethooton_ @ErinInTheMorn @fifi_EY 4/…as many other staff at their trust wrote⬇️ to the press in 2002 (when the first instigator of this case, psychoanalyst Susan Evans was on staff too) that no trans people should be allowed that recognition but needed

@janethooton_ @ErinInTheMorn @fifi_EY 5/…to "cure" us instead. Yet GIDS proved incapable of defending its super-conservative protocol in court - no doubt because GIDS has always expected challenges to be from patients seeking care more like that elsewhere, arrogantly ignoring that services in countries where the…
Thread on how atheism leads to mental retardation (backed with medical citations🧵💉)

To start with, atheism is an unnatural self-contradicting doctrine.

Medical terminology proves that human beings are naturally pre-disposed to believe in God. Oxford scientists assert that people are "born believers".

https://t.co/kE0Fi588yn
https://t.co/OqyXcGIMJn


It should be known that atheism could never produce an intelligently-functioning society and neither ever will.

Contrastingly, Islam produced several intellectuals & polymaths, was on the forefront of scientific development, boasting 100% literacy


It is also scientifically proven that atheism led to lesser scientific curiosity and scientific frauds, which is also why atheists incline to pseudo-science.

Whereas, religion in general and Islam in particular boosted education.

https://t.co/19Onc84u3g


Atheists are also likely to affected by pervasive mental and developmental disorders like high-functioning autism.

Cognitive Scientists and renowned Neurologists found that more atheism is leads to greater autism.

https://t.co/zRjEyFoX3P
@SMILEWithmeNGO Hello @SMILEWithmeNGO I am glad to be here. Thank you for having me.

A very big welcome to everyone joining today’s conversation. Our guest today needs no introduction especially in the sphere of cancer control and advocacy. Welcome @runciecwc
#CheatCervicalCancer


@runciecwc Q1: So Runcie @runciecwc, we see all the amazing work you do as an advocate.
Can you share with us some of the work that you have been doing in cancer control in Nigeria?
#CheatCervicalCancer

@runciecwc That’s amazing. Your work speaks for you. Thanks for all you do.
Q2: What is this @WHO Global Strategy to accelerate the Elimination of CervicalCancer? Can you elaborate on it?
#CheatCervicalCancer

@runciecwc @WHO Q3: In your experience, so far what are the greatest challenges you have identified with cancer control in Nigeria?
#CheatCervicalCancer.

@runciecwc @WHO Q4: Interestingly, we have seen that your organization is part of the Coalition of CSOs against Cervical Cancer in Nigeria, @CervicalCancerN, what is the goal of this Coalition? #CheatCervicalCancer

You May Also Like

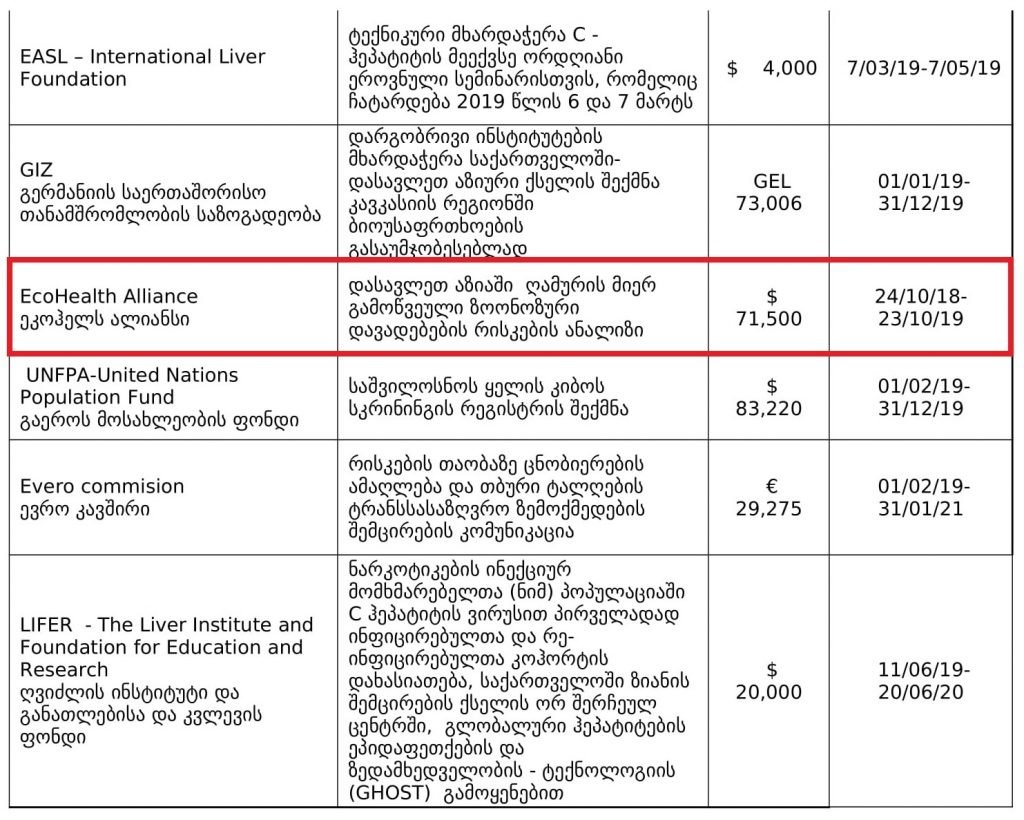
1. Project 1742 (EcoHealth/DTRA)
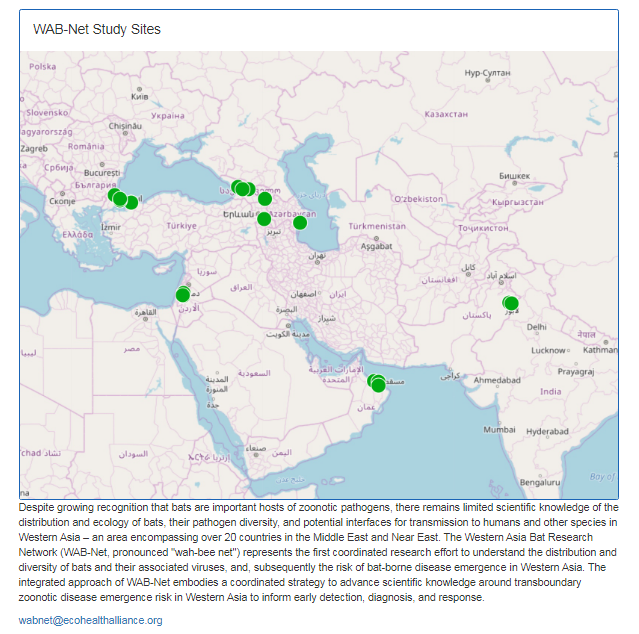
Risks of bat-borne zoonotic diseases in Western Asia

Duration: 24/10/2018-23 /10/2019

Funding: $71,500
@dgaytandzhieva
https://t.co/680CdD8uug


2. Bat Virus Database
Access to the database is limited only to those scientists participating in our ‘Bats and Coronaviruses’ project
Our intention is to eventually open up this database to the larger scientific community
https://t.co/mPn7b9HM48


3. EcoHealth Alliance & DTRA Asking for Trouble
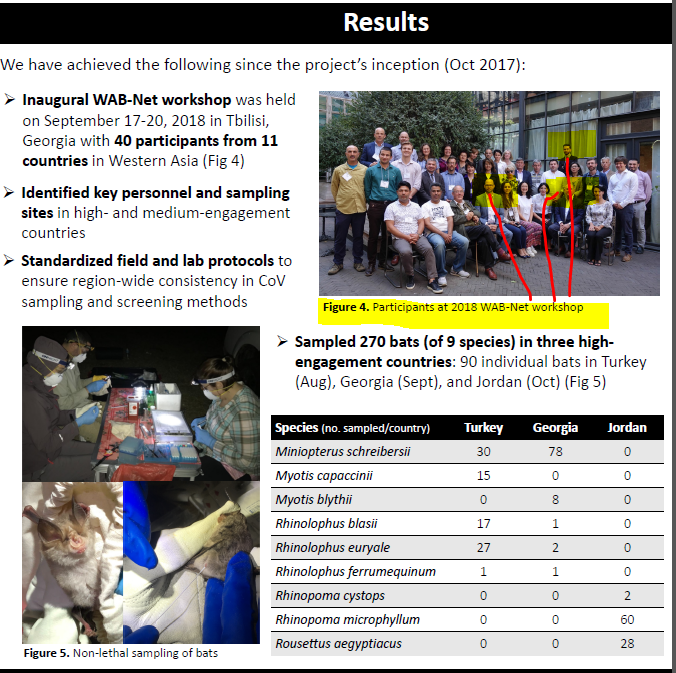
One Health research project focused on characterizing bat diversity, bat coronavirus diversity and the risk of bat-borne zoonotic disease emergence in the region.
https://t.co/u6aUeWBGEN


4. Phelps, Olival, Epstein, Karesh - EcoHealth/DTRA


5, Methods and Expected Outcomes
(Unexpected Outcome = New Coronavirus Pandemic)
A THREAD ON @SarangSood

Decoded his way of analysis/logics for everyone to easily understand.

Have covered:
1. Analysis of volatility, how to foresee/signs.
2. Workbook
3. When to sell options
4. Diff category of days
5. How movement of option prices tell us what will happen

1. Keeps following volatility super closely.

Makes 7-8 different strategies to give him a sense of what's going on.

Whichever gives highest profit he trades in.


2. Theta falls when market moves.
Falls where market is headed towards not on our original position.


3. If you're an options seller then sell only when volatility is dropping, there is a high probability of you making the right trade and getting profit as a result

He believes in a market operator, if market mover sells volatility Sarang Sir joins him.


4. Theta decay vs Fall in vega

Sell when Vega is falling rather than for theta decay. You won't be trapped and higher probability of making profit.