I've seen many news articles cite that "the UK variant could be the dominant strain by March". This is emphasized by @CDCDirector.

While
this will likely to be the case, this should not be an automatic cause for concern. Cases could still remain contained.

Here's how: 🧵

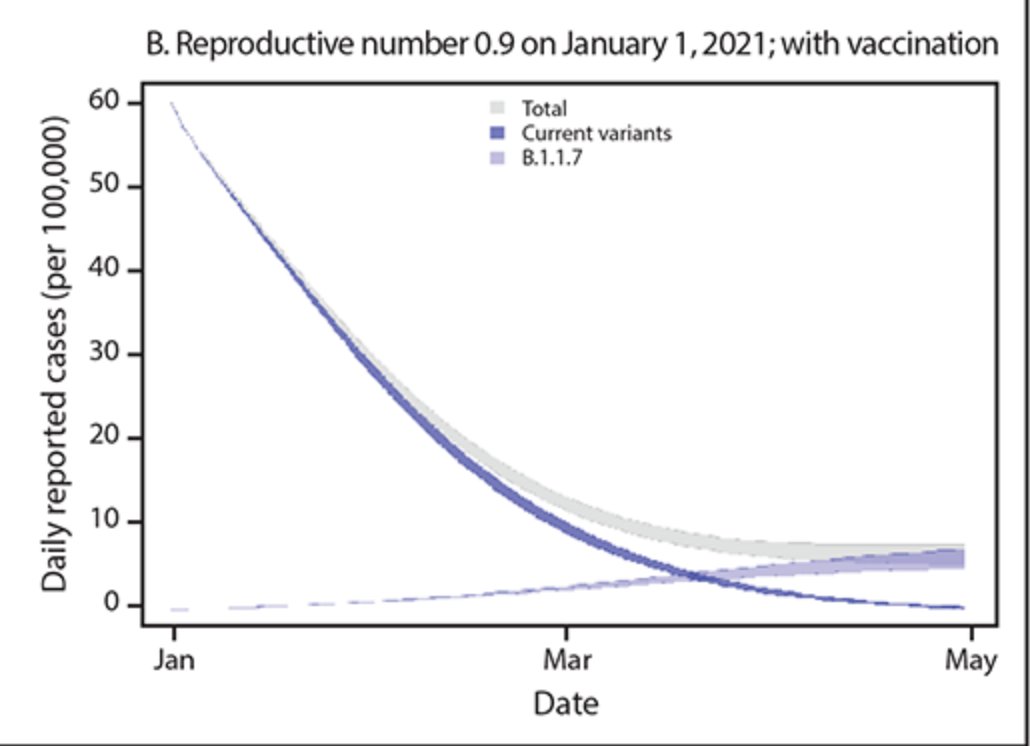
One of @CDCgov's own models has tracked the true decline in cases quite accurately thus far.

Their projection shows that the B.1.1.7 variant will become the dominant variant in March. But interestingly... there's no fourth wave. Cases simply level out:

https://t.co/tDce0MwO61
Just because a variant becomes the dominant strain does not automatically mean we will see a repeat of Fall 2020.

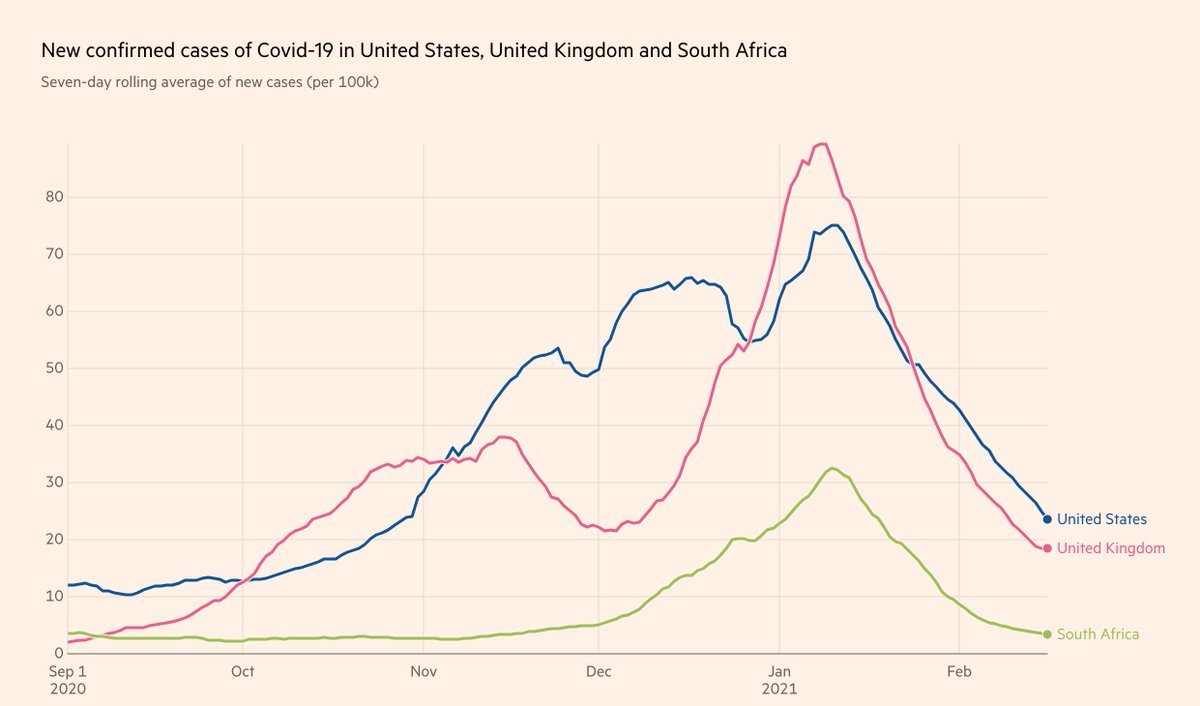
Let's look at UK and South Africa, where cases have been falling for the past month, in unison with the US (albeit with tougher restrictions):
Furthermore, the claim that the "variant is doubling every 10 days" is false. It's the *proportion of the variant* that is doubling every 10 days.

If overall prevalence drops during the studied time period, the true doubling time of the variant is actually much longer 10 days.
Simple example:

Day 0: 10 variant / 100 cases -> 10% variant
Day 10: 15 variant / 75 cases -> 20% variant
Day 20: 20 variant / 50 cases -> 40% variant

1) Proportion of variant doubles every 10 days
2) Doubling time of variant is actually 20 days
3) Total cases still drop by 50%
Given these facts, I think headlines along the lines of "CDC warns UK variant could be dominant strain by March" can be misleading.

It has the consequence of instilling fear in the public, who are much more likely to misinterpret it as "there will be another bad wave".
The amount of pessimism still present and being proliferated does not match a reality where:

1) Cases and hospitalizations have fallen by more than half in the past month (and still falling)
2) We have administered the vaccine to 40M+ people, with 1M new vaccinations per day
Of course, there's a very possible scenario that we'll see a fourth wave beginning in mid/late March and peaking in April/May. I'm not trying to downplay that.

But I'm baffled to see such a high level of confidence from the public health community that a fourth wave will happen.
I was told last year that the purpose of restrictions/interventions is to "flatten the curve". That the main goal is to make sure we do not overwhelm our healthcare system.

That messaging seems to have been shifted to "eliminate the curve". Why?
It's possible that selection bias may be at play (i.e. experts that are more confident about a fourth surge will have their voices amplified).

In any case, the future trajectory of the variant is still unclear, at least from the data. It's good to tread with cautious optimism.

More from Society

You May Also Like

1/“What would need to be true for you to….X”

Why is this the most powerful question you can ask when attempting to reach an agreement with another human being or organization?

A thread, co-written by @deanmbrody:


2/ First, “X” could be lots of things. Examples: What would need to be true for you to

- “Feel it's in our best interest for me to be CMO"
- “Feel that we’re in a good place as a company”
- “Feel that we’re on the same page”
- “Feel that we both got what we wanted from this deal

3/ Normally, we aren’t that direct. Example from startup/VC land:

Founders leave VC meetings thinking that every VC will invest, but they rarely do.

Worse over, the founders don’t know what they need to do in order to be fundable.

4/ So why should you ask the magic Q?

To get clarity.

You want to know where you stand, and what it takes to get what you want in a way that also gets them what they want.

It also holds them (mentally) accountable once the thing they need becomes true.

5/ Staying in the context of soliciting investors, the question is “what would need to be true for you to want to invest (or partner with us on this journey, etc)?”

Multiple responses to this question are likely to deliver a positive result.