“Should I give them more fluid?”

Extremely common question during AKI referrals from junior docs.

⛔️ Fluid management is tricky, often misunderstood, & can cause huge iatrogenic harm ⛔️

We try to convey important principles in THREAD 👇

#tipsfornewdocs #medtwitter #tweetorial

Currently too often patients with high creatinine are given too much IV fluid, driven by an AKI ➡️ fluid reflex

We’ve seen 7 litres be given in one shift.

Medics & surgeons, juniors & seniors, it seems everyone loves to reach for extra IV fluid (especially if urine output poor)
Why does huge volume IV fluid ‘resuscitation’ consistently occur?

Lots of reasons, including FALSE beliefs:
🛑 IV fluid always “treats AKI”
🛑 Hypotension = hypovolaemia
🛑 Lactate >2 means fluid deficiency
🛑 Septic patients are very hypovolaemic
The rule with IV fluids and AKI is to remember this 5 word phrase:

💥 💥 Aim for euvolaemia, then stop💥 💥

Fluid status is like Goldilocks - hypovolaemia is bad for the kidneys BUT excess volume is also harmful for renal function and will cause other complications too.
It is easy to say “target euvolaemia” - but we agree it is more difficult to do!

Fluid status assessment is certainly made harder by a belief that we must only rely on a snapshot assessment of examination features which are NOT specific / sensitive / reliable to elicit like.…
🔹 Cool peripheries
🔹 Bibasal crackles - highly nonspecific in older patients!
🔹 Dry skin
🔹Tachycardia
🔹 x and y descent of the JVP wave…..

Even postural BP drop, one of the better performing signs for hypovolaemia, still has a wide differential diagnosis.
Serial physical examinations by one clinician improves assessment, but this is challenging given shift patterns.

And unfortunately the blood tests can be misleading too - for example check out our previous post about other causes of raised urea 👇 https://t.co/CSiRRnMi1a
TIP - things get better when the adage of ‘history trumps examination’ is observed:

1️⃣ Has there been volume loss?
2️⃣ Has there been decreased intake?

If the answer is “not really” to both of these, then think carefully about what you think more fluid will accomplish.
So….

When phoned as renal reg on-call on day 2-3 we’re usually not thinking “easy hypovolaemic AKI” but are concerned something is being missed.

Three common things:

1. AKI is part of sepsis / hypotension / MOF badness: patient needs ICU & vasopressors, not more IV fluid
2. AKI is intrinsic or post-renal: patient needs a diagnosis (think urinalysis, ultrasound, discussion), not more IV fluid

3. AKI is an additional signal that palliative care may be appropriate (remember stage 3 AKI has terrible 42% mortality at 30 days in patients >75 years)
Pre-renal AKI purely due to hypovolaemia generally improves fast.

If the patient has a great story for hypovolaemia but their creatinine is rising/stuck, then they often have a degree of acute tubular necrosis (ATN).

Let us show you something (it’s not as boring as it appears!)
On left is ATN with gaping spaces in tubules, & on right is healthy kidney with nice plump tubules.

Appreciate that there is actual histological change - this needs TIME to recover

✳️ Just as injured cells in stroke or MI don’t magically heal with IV saline, neither does ATN ✳️
✅ Sometimes you’ll get a patient with ATN to euvolaemia & they still won’t pee. That’s OK - not an indication for more fluids

✅ Remember low urine output is a warning you have less margin for error before causing hypervolaemia - again, shake off the reflex just to ⬆️fluid rate
“Are there exceptions?”

Not really - there’s different risk:benefit in different scenarios
👉 in tumour lysis, myeloma or rhabdo for example we do try to target higher urine outputs

BUT when patient is well-filled & not peeing much, we’re re-thinking rather than ploughing on.
“But does volume overload even matter?”

YES - and it’s not just the obvious pulmonary oedema badness.

Excess fluid ➡️ high venous pressure ➡️ decreased perfusion pressure for heart, brain, liver (& kidneys!!)

Patients with excess volume have:
🛑 longer AKI
🛑 higher mortality
In hypovolaemic AKI aim to stop fluids before complications develop - you do not need to “swell to get well”.

Avoidable dialysis for ⬆️volume continues because of myth that the hugely complex pathophysiology of AKI is easily remedied by IV salty water (pic from Ostermann et al)
So apologies for the rant. But we hope we have made you think about why:

🛑 “I can’t give fluid for their AKI because they are already overloaded” makes no sense 🛑

And why:

🛑 “I’ll keep giving IV fluids until their oxygen sats drop” is just bonkers 🛑
Take home points:

✅ Prescribe IV fluid with the care you would warfarin
✅ Achieve euvolaemia, then sit on your hands
✅ If urine output or BP stays low think “Is a different approach needed here?” rather than autoreaching for more IV fluid
✅ Break your AKI ➡️ fluid reflex
As ever all comments/disagreements very welcome - it’s a tricky topic to teach & not done really at med school, so we at @BukuRenal (@jamiekwillows this time) appreciate any feedback.

Would love to hear views on how you approach teaching ward junior docs @NephroGuy @icmteaching

More from Health

No-regret #hydrogen:
Charting early steps for H₂ infrastructure in Europe.

👉Summary of conclusions of a new study by @AgoraEW @AFRY_global @Ma_Deutsch @gnievchenko (1/17)
https://t.co/YA50FA57Em


The idea behind this study is that future hydrogen demand is highly uncertain and we don’t want to spend tens of billions of euros to repurpose a network which won’t be needed. For instance, hydrogen in ground transport is a hotly debated topic
https://t.co/RlnqDYVzpr (2/17)

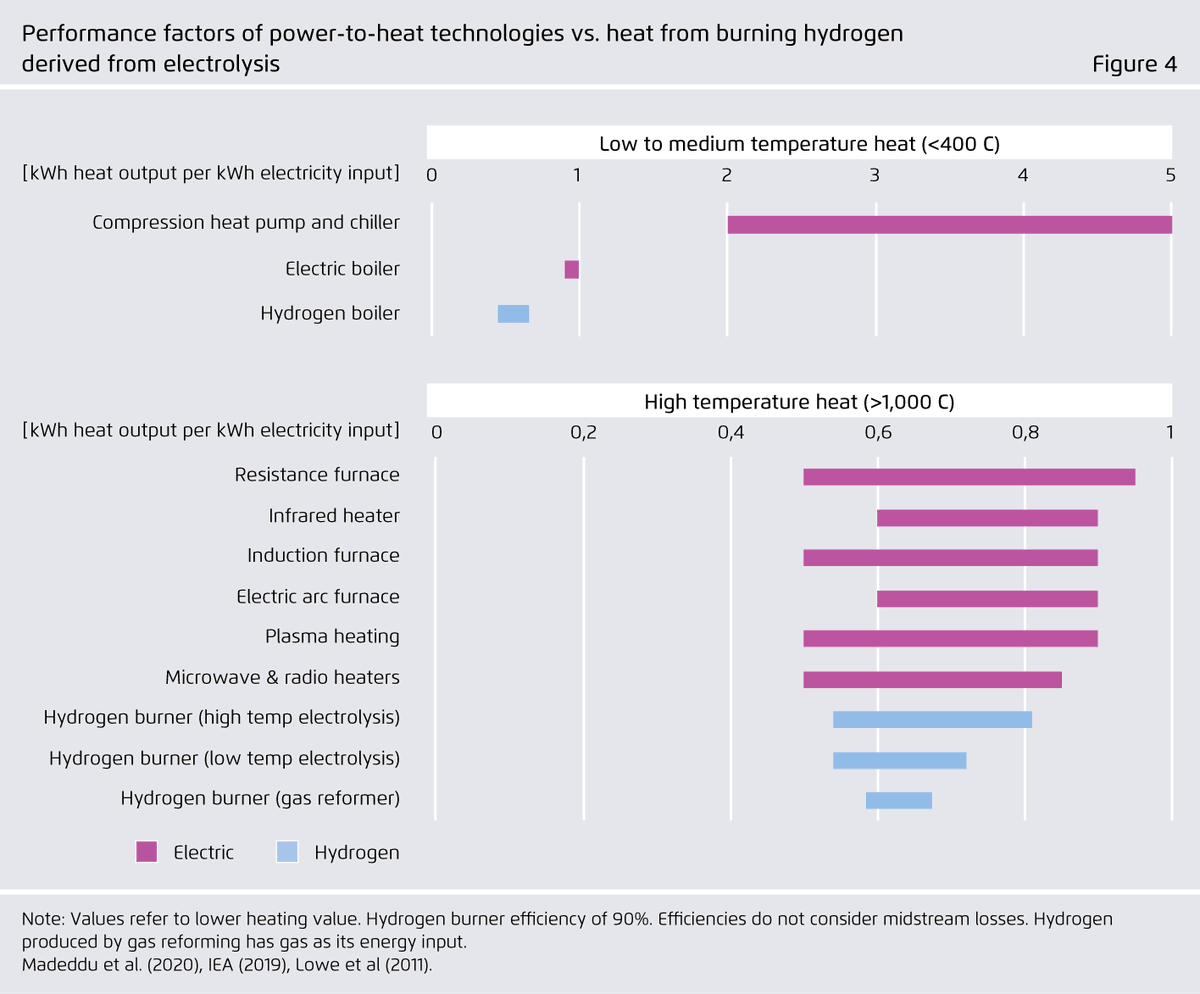
Similar things can be said about heat. 40% of today’s industrial natural gas use in the EU goes to heat below 100°C and therefore is within range of electric heat pumps – whose performance factors far exceed 100%. (3/17)


Even for higher temperatures, a range of power-to-heat (PtH) options can be more energy-efficient than hydrogen and should be considered first. Available PtH technologies can cover all temperature levels needed in industrial production (e.g. electric arc furnace: 3500°C). (4/17)


In our view, hydrogen use for feedstock and chemical reactions is the only inescapable source of industrial hydrogen demand in Europe that does not lend itself to electrification. Examples include ammonia, steel, and petrochemical industries. (5/17)

You May Also Like

1/12

RT-PCR corona (test) scam

Symptomatic people are tested for one and only one respiratory virus. This means that other acute respiratory infections are reclassified as


2/12

It is tested exquisitely with a hypersensitive non-specific RT-PCR test / Ct >35 (>30 is nonsense, >35 is madness), without considering Ct and clinical context. This means that more acute respiratory infections are reclassified as


3/12

The Drosten RT-PCR test is fabricated in a way that each country and laboratory perform it differently at too high Ct and that the high rate of false positives increases massively due to cross-reaction with other (corona) viruses in the "flu


4/12

Even asymptomatic, previously called healthy, people are tested (en masse) in this way, although there is no epidemiologically relevant asymptomatic transmission. This means that even healthy people are declared as COVID


5/12

Deaths within 28 days after a positive RT-PCR test from whatever cause are designated as deaths WITH COVID. This means that other causes of death are reclassified as
This is NONSENSE. The people who take photos with their books on instagram are known to be voracious readers who graciously take time to review books and recommend them to their followers. Part of their medium is to take elaborate, beautiful photos of books. Die mad, Guardian.


THEY DO READ THEM, YOU JUDGY, RACOON-PICKED TRASH BIN


If you come for Bookstagram, i will fight you.

In appreciation, here are some of my favourite bookstagrams of my books: (photos by lit_nerd37, mybookacademy, bookswrotemystory, and scorpio_books)
Margatha Natarajar murthi - Uthirakosamangai temple near Ramanathapuram,TN
#ArudraDarisanam
Unique Natarajar made of emerlad is abt 6 feet tall.
It is always covered with sandal paste.Only on Thriuvadhirai Star in month Margazhi-Nataraja can be worshipped without sandal paste.


After removing the sandal paste,day long rituals & various abhishekam will be
https://t.co/e1Ye8DrNWb day Maragatha Nataraja sannandhi will be closed after anointing the murthi with fresh sandal paste.Maragatha Natarajar is covered with sandal paste throughout the year


as Emerald has scientific property of its molecules getting disturbed when exposed to light/water/sound.This is an ancient Shiva temple considered to be 3000 years old -believed to be where Bhagwan Shiva gave Veda gyaana to Parvati Devi.This temple has some stunning sculptures.
@EricTopol @NBA @StephenKissler @yhgrad B.1.1.7 reveals clearly that SARS-CoV-2 is reverting to its original pre-outbreak condition, i.e. adapted to transgenic hACE2 mice (either Baric's BALB/c ones or others used at WIV labs during chimeric bat coronavirus experiments aimed at developing a pan betacoronavirus vaccine)

@NBA @StephenKissler @yhgrad 1. From Day 1, SARS-COV-2 was very well adapted to humans .....and transgenic hACE2 Mice


@NBA @StephenKissler @yhgrad 2. High Probability of serial passaging in Transgenic Mice expressing hACE2 in genesis of SARS-COV-2


@NBA @StephenKissler @yhgrad B.1.1.7 has an unusually large number of genetic changes, ... found to date in mouse-adapted SARS-CoV2 and is also seen in ferret infections.
https://t.co/9Z4oJmkcKj


@NBA @StephenKissler @yhgrad We adapted a clinical isolate of SARS-CoV-2 by serial passaging in the ... Thus, this mouse-adapted strain and associated challenge model should be ... (B) SARS-CoV-2 genomic RNA loads in mouse lung homogenates at P0 to P6.
https://t.co/I90OOCJg7o